An atrioventricular block is a delay or interruption in conduction from the atria toward the ventricles. On a rhythm strip, that means the relationship between P waves and QRS complexes carries most of the evidence.
The evidence to collect first
- Are the P waves regular?
- Is the PR interval normal or prolonged?
- Does the PR interval stay constant or change?
- Does every P wave conduct to a QRS?
- Are there two or more consecutive nonconducted P waves?
- Do P waves and QRS complexes have any consistent relationship?
The NCBI Bookshelf overview of AV block describes a typical PR interval as 0.12 to 0.20 seconds and classifies blocks by the delay or interruption in atrioventricular conduction.
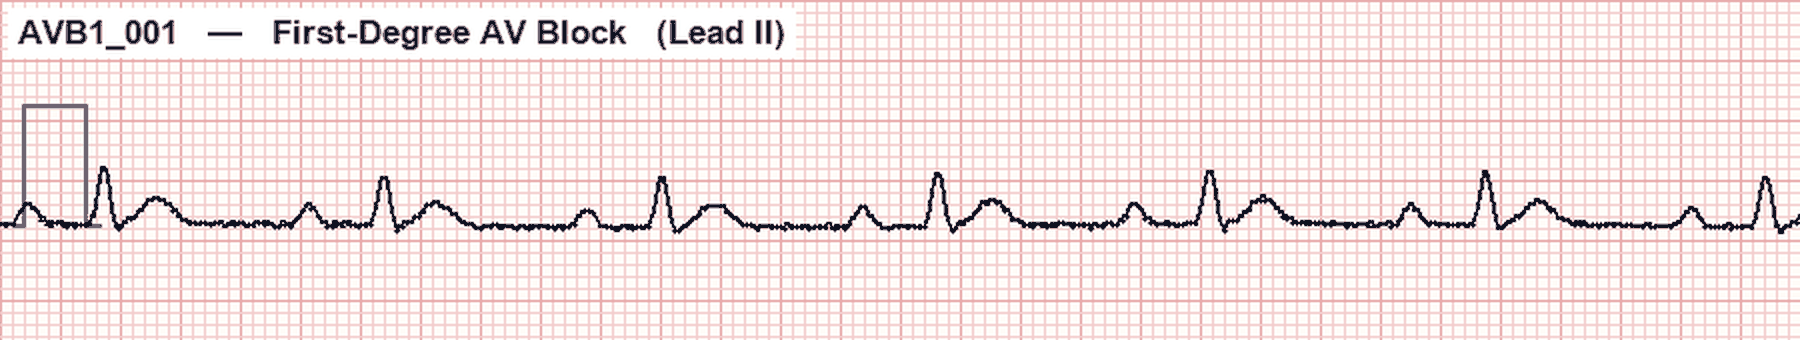
First-degree AV block
Every atrial impulse conducts, but conduction is delayed. The visible pattern is a PR interval longer than 0.20 seconds that remains constant, followed by a QRS for every P wave.
The name can be misleading for beginners because no beat is actually dropped. The useful description is: prolonged, constant PR interval with one-to-one conduction.
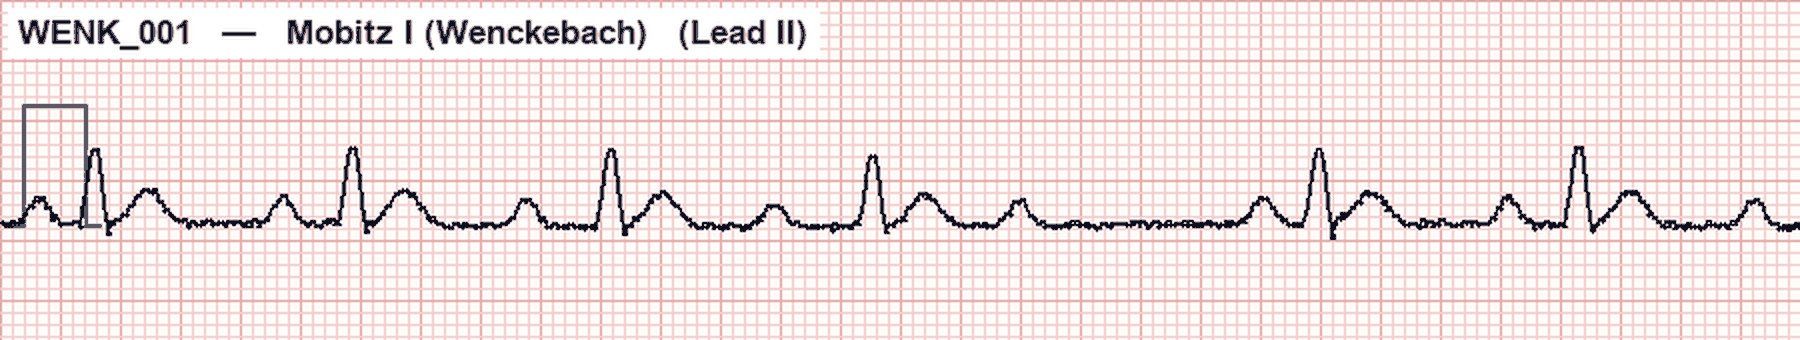
Second-degree AV block, Mobitz I (Wenckebach)
The PR interval progressively lengthens across conducted beats until a P wave is not followed by a QRS. After the dropped beat, the sequence resets and begins again.
Do not rely on the pause alone. The evidence is the changing PR interval before the nonconducted P wave. Compare several conducted beats so the progression is visible.
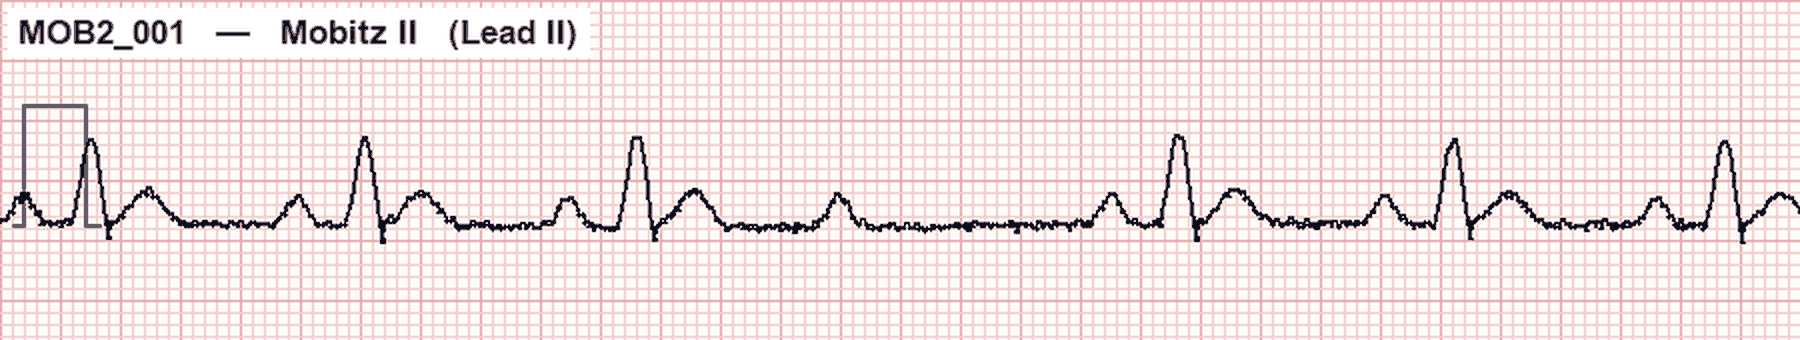
Second-degree AV block, Mobitz II
Conducted beats have constant PR intervals, but an atrial impulse intermittently fails to conduct. The nonconducted P wave appears without the progressive PR prolongation seen in Wenckebach.
The NCBI review emphasizes that at least two consecutive conducted P waves are needed to demonstrate constant PR intervals and distinguish Mobitz II from Wenckebach. That is one reason a short or incomplete strip can be misleading.
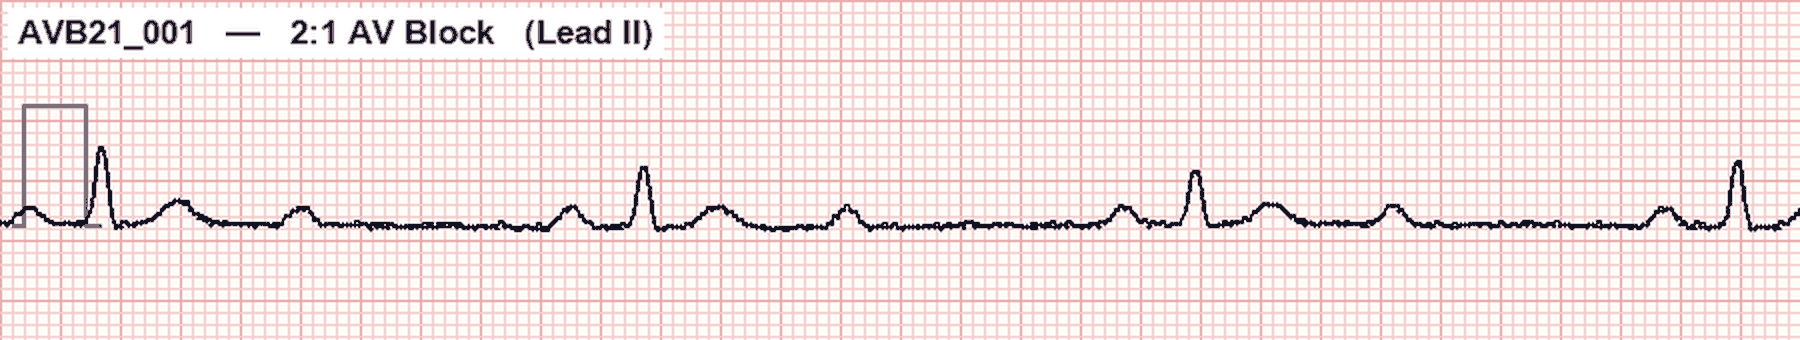
2:1 AV block vs Mobitz II and high-grade block
Can a 2:1 AV block be called Mobitz II? Usually not from a short rhythm strip alone. When every other P wave is nonconducted, there are not enough consecutive conducted beats to determine whether the PR pattern follows Mobitz I or Mobitz II criteria. A 2024 peer-reviewed review of Mobitz II misclassification recommends describing the visible evidence as 2:1 AV block instead of forcing a subtype.
High-grade AV block refers to two or more consecutive nonconducted P waves while some atrioventricular conduction remains. It is different from complete heart block because at least some atrial impulses still conduct.
Third-degree (complete) AV block
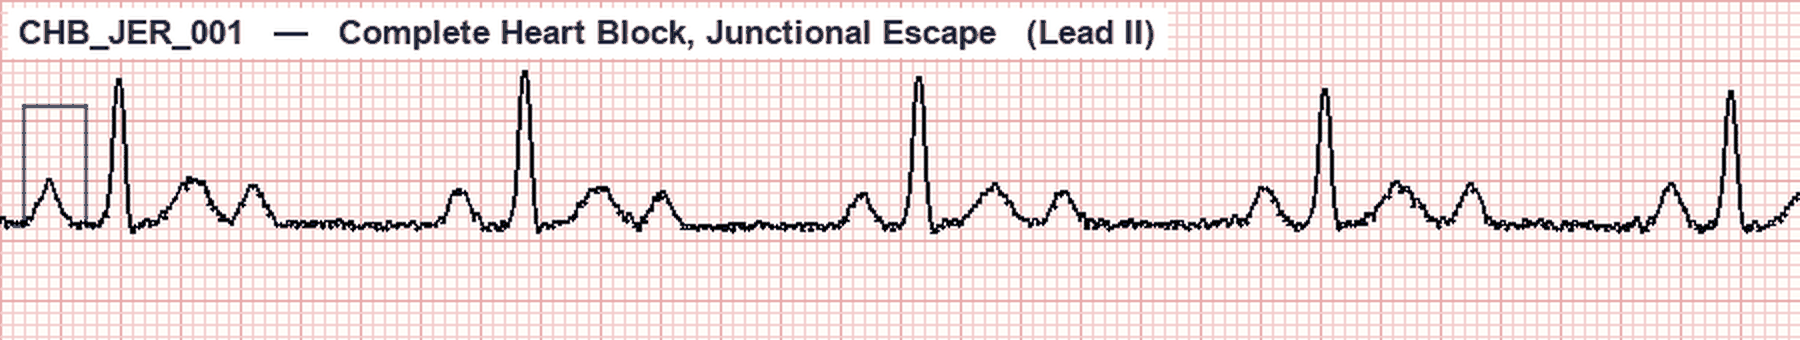
In complete heart block, atrial impulses do not conduct to the ventricles. P waves continue at their own rate, while the ventricles are activated by an escape rhythm. The atrial and ventricular rhythms are independent.
Look for regular P-P intervals, regular or near-regular R-R intervals, and PR intervals that vary because the P waves and QRS complexes are not linked. The defining evidence is atrioventricular dissociation, not simply a slow rate.
Quick comparison
| Pattern | PR interval | Conduction evidence |
|---|---|---|
| First-degree | Prolonged and constant | Every P wave conducts |
| Mobitz I | Progressively lengthens | P wave eventually fails to conduct, then sequence resets |
| Mobitz II | Constant on conducted beats | Intermittent nonconducted P waves without progressive prolongation |
| 2:1 AV block | Subtype may be indeterminate | Every other P wave conducts |
| High-grade AV block | Assess conducted beats | Two or more consecutive P waves fail to conduct |
| Third-degree | Variable with no fixed relationship | Atria and ventricles activate independently |
Common interpretation pitfalls
- Calling any pause Wenckebach without demonstrating progressive PR prolongation.
- Calling a 2:1 pattern Mobitz II when the strip does not show enough conducted beats to classify it.
- Confusing blocked premature atrial complexes with AV block.
- Using ventricular rate alone to identify complete heart block.
- Ignoring artifact or P waves hidden in T waves.
Why clinical context matters
The 2018 ACC/AHA/HRS guideline on bradycardia and conduction delay addresses evaluation and management using symptoms, reversible causes, conduction level, and the broader clinical picture. A monitor strip can raise concern, but clinical decisions require more than a pattern label.
Sources
- NCBI Bookshelf: Atrioventricular Block
- NCBI Bookshelf: Second-Degree Atrioventricular Block
- Mobitz Type II Second-Degree Atrioventricular Block: A Commonly Overdiagnosed and Misinterpreted Arrhythmia
- ACC/AHA/HRS Guideline on Bradycardia and Cardiac Conduction Delay
Educational use only. This article does not replace patient assessment, clinical judgment, formal training, current guidelines, or facility protocols.